
Routine imaging already contains preventive health information that patients often never receive. Artificial intelligence is making it possible to surface that information consistently, at scale, and without adding new scans, new radiation, or new appointments.
A classic example comes from the Pickhardt expert panel review. A 77-year-old woman underwent abdominal CT for flank pain, a stone was identified. The stone explained the patient’s symptoms, but it was only one part of what the scan revealed. Osteoporotic bone loss, sarcopenia and severe aortic calcification were also visible: findings with potential implications for her health. Until recently, measuring and reporting all of them routinely would have demanded more time than most radiology workflows could accommodate. That is the clinical problem opportunistic screening is meant to solve.
What falls under the scope of opportunistic screening
In radiology, opportunistic screening means systematically extracting clinically relevant biomarkers from imaging performed for another indication. It differs from an incidentaloma, which is a focal unexpected finding discovered by chance. Opportunistic screening is deliberate: the same scan is read with a second, structured lens for conditions that are common, often asymptomatic until later stages, and potentially modifiable if detected early.
This distinction matters because opportunistic screening is about converting routine imaging into preventive data. In practice, that means using explainable AI and structured workflows to quantify measures such as trabecular attenuation, coronary calcium, liver attenuation, muscle density, or bone health markers without adding meaningful time to the report.
CT’s role in opportunistic screening
In practice, body CT has been the most established and practical modality for opportunistic screening because of its rich quantitative data.
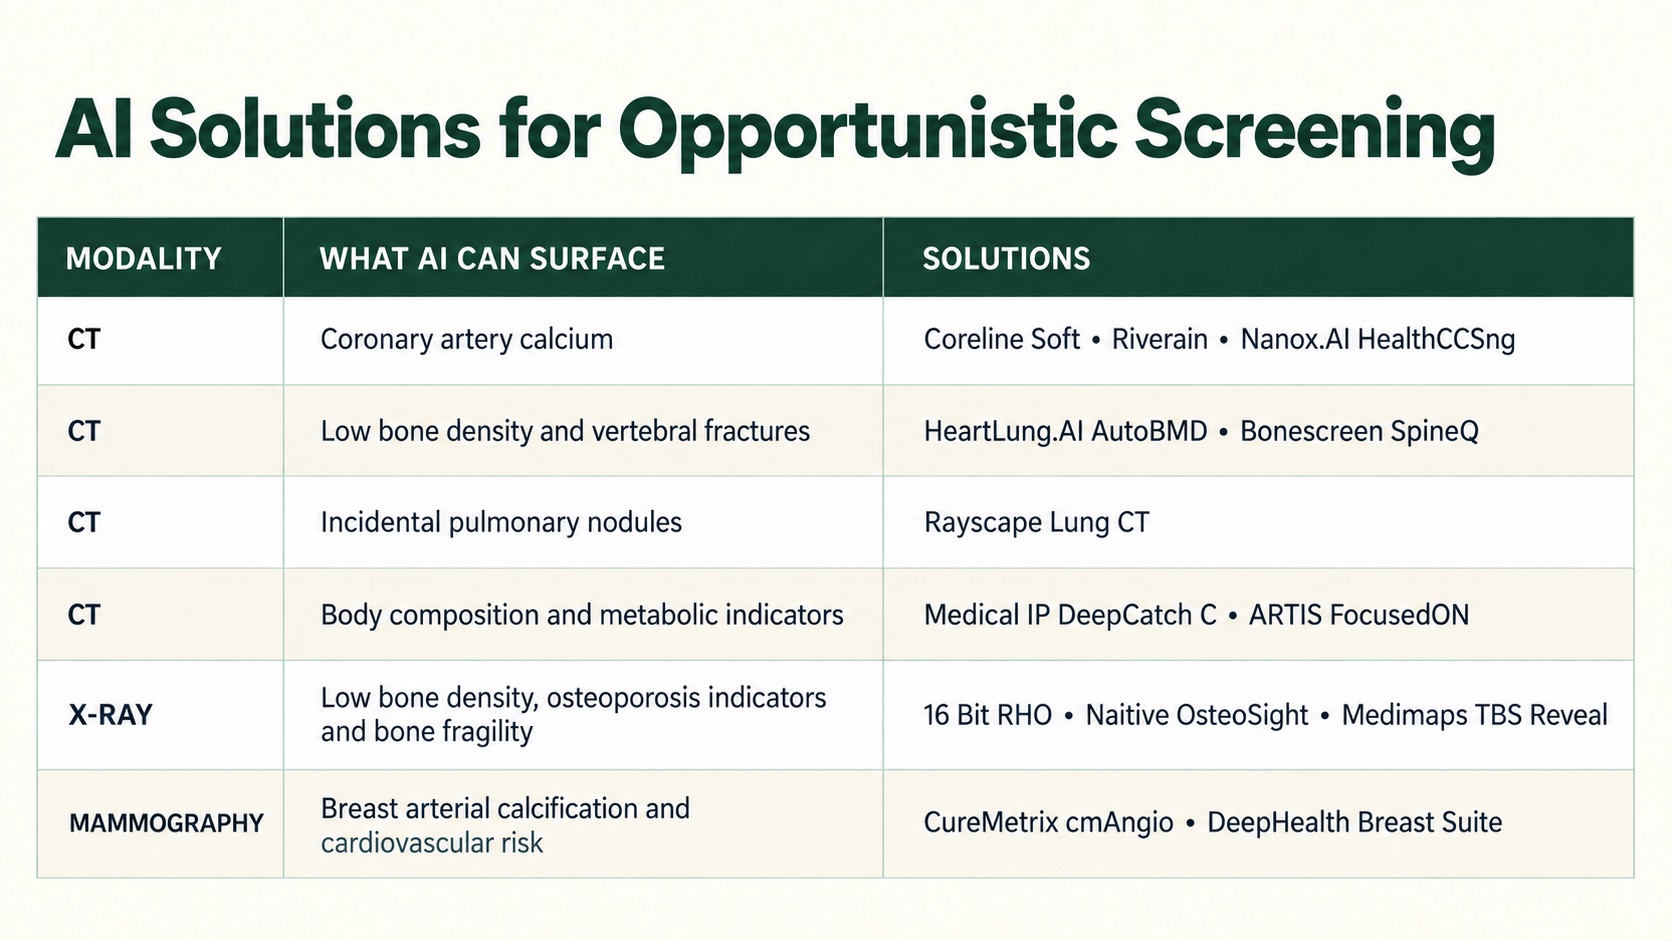
Solutions from Coreline, Riverain, and Nanox support opportunistic coronary calcium assessment on non-gated chest CT, with automated or semi-automated Agatston scoring that can be incorporated into routine reporting.
Opportunistic osteoporosis screening can be performed from abdominal or thoracic CT studies, and tools such as Heartlung.ai AutoBMD and SpineQ Bonescreen are aimed at turning routine CT into a bone mineral density assessment workflow. AutoBMD detects the vertebral column, labels vertebral levels, identifies the trabecular region, and reports BMD-related outputs, while SpineQ adds level-wise annotation, calibrated BMD, and fracture identification.
Routine CT often captures the lungs even when the scan was ordered for something else, which means incidental pulmonary nodules can be present and clinically relevant. AI tools like Rayscape Lung CT help detect, measure, and classify these nodules more consistently so they can enter a structured follow-up pathway rather than being noted only in passing. Lung cancer remains one of the leading causes of cancer death globally, and many patients encounter imaging before they ever enter a formal screening program. Opportunistic detection may help close that gap.
X-ray
Plain radiography offers another important opportunity. Chest, spine, pelvis, and extremity radiographs are acquired in enormous volumes every day, yet the bone-health information they contain is often not captured in a structured way. The companies working in this area are broadly aligned but not identical in focus: RHO (16bit) is positioned around opportunistic bone mineral density screening from routine X-rays, Naitive Tech’s OsteoSight is aimed at identifying musculoskeletal radiographs with evidence of osteoporosis, and Medimaps’ TBS Reveal moves toward AI-enabled assessment of bone fragility from standard radiographs.
These tools can help flag patients with low bone density or elevated fracture risk who might otherwise never be referred for dedicated DXA, using imaging that has already been acquired.
Mammography and vascular risk
Breast arterial calcification is a marker of systemic vascular disease in women, yet it remains underreported in many practices. The Canadian Society of Breast Imaging has issued a position statement supporting the reporting of breast arterial calcification on mammography, reinforcing its value beyond breast cancer detection.
That is why cmAngio by CureMetrix and Breast Suite by DeepHealth are important examples of opportunistic screening in breast imaging. It identifies and quantifies breast arterial calcifications on mammography and digital breast tomosynthesis, enabling radiologists to communicate a cardiovascular risk marker without additional radiation or a separate exam.
Multi-organ opportunistic CT
Some tools go beyond single-biomarker use cases and move toward more comprehensive body composition analysis. DeepCatch C by Medical IP is one such example. It auto-segments structures including skin, bone, muscle, visceral fat, subcutaneous fat, and internal organs from CT images, which makes it useful for broader opportunistic screening and body composition assessment.
Another partner in this space is ARTIS Development, whose AI-driven CT body composition analysis tool - FocusedON, reflects the broader shift toward opportunistic nutritional and metabolic screening from imaging already being performed.
This matters because many patients do not have one isolated risk factor. They have a cluster of findings: central adiposity, low muscle density, hepatic steatosis, calcified plaque, and bone loss. Multi-organ tools help radiologists see that cluster more clearly, especially when the goal is not just detection, but risk profiling.
What AI changes in practice
The practical barrier has always been scale. Manual quantification is very much possible, but it might be too slow to fit into everyday practice across high-volume departments. AI changes that by automating segmentation, measurement, and report generation, while providing quality assurance images that let radiologists verify the result quickly before sign-off.
This is also where structured reporting matters. Opportunistic findings need to be visible, actionable, and easy to communicate to referring clinicians. A score that is generated but never integrated into the report has limited clinical value.
The future of opportunistic screening is collaborative, with human interpretation and algorithmic precision working together. Opportunistic screening is not just clinically valuable, it is commercially opportune as well, with reimbursement pathways and downstream revenue potential for institutions.
Why this matters for CARPL
Opportunistic screening only works when validated algorithms are available in a workflow that radiologists can actually use, trust, and monitor over time. A platform approach lets departments compare solutions across use cases, route outputs into reporting, and maintain oversight as the AI footprint expands.
That is the real opportunity: not simply to buy algorithms, but to build a dependable operational layer around them. In opportunistic screening, the scan has already been acquired. What changes is whether the hidden clinical value inside that scan is systematically surfaced, reported, and acted upon. CARPL is well positioned to make that shift practical across modalities and vendors.
References
Pickhardt PJ, Summers RM, Garrett JW, Krishnaraj A, Agarwal S, Dreyer KJ, Nicola GN. Opportunistic Screening: Radiology Scientific Expert Panel. Radiology. 2023;307(5):e222044.
Pickhardt PJ, Lee MH, Warner JD, Summers RM, Garrett JW. CT-based Opportunistic Screening for Adding Clinical Value: How I Do It. Radiology. 2026;319(1):e252106.
Pickhardt PJ, Correale L, Hassan C. AI-based opportunistic CT screening of incidental cardiovascular disease, osteoporosis, and sarcopenia: cost-effectiveness analysis. Abdom Radiol. 2023;48:1181–1198.
Canadian Society of Breast Imaging. Position statement on reporting breast arterial calcification on mammography.
Rayscape Lung CT product information and website.
